Tumor Microenvironment (TME): Immune Cells, CAFs, Hypoxia, Metabolism & Cancer Treatment Resistance (2026)
The tumor microenvironment (TME) is the biological ecosystem surrounding a tumor. It includes immune cells, cancer-associated fibroblasts, blood and lymphatic vessels, extracellular matrix, signaling molecules, nutrients, metabolites and physical conditions such as hypoxia, acidity and abnormal tissue pressure.
Modern oncology increasingly recognizes that cancer is not simply a collection of abnormal cells. Tumor cells continually interact with the tissues around them, and those interactions can influence tumor growth, invasion, metastasis, immune surveillance, drug delivery and treatment response.
The National Cancer Institute defines the tumor microenvironment as the normal cells, molecules and blood vessels that surround and feed tumor cells, while emphasizing that tumors can change their microenvironment and that the microenvironment can in turn affect how tumors grow and spread.
Key idea: A tumor's biology is partly determined by the tumor cells themselves and partly by the environment in which those cells live.
This makes the TME an important bridge between several major areas of modern cancer research:
Cancer metabolism Immunotherapy Biomarkers Drug delivery Hypoxia Tumor immunity Treatment resistance Metastasis Spatial oncology
Important: Not all cancers have the same TME. The microenvironment can differ between cancer types, between patients with the same cancer, between different lesions in the same patient and even between regions of a single tumor.
Table of Contents
- What Is the Tumor Microenvironment?
- The Major Components of the TME
- The Tumor Immune Microenvironment
- Cancer-Associated Fibroblasts and Extracellular Matrix
- Tumor Blood Vessels and Vascular Dysfunction
- Hypoxia and HIF Signaling
- The Metabolic TME: Glucose, Lactate, Adenosine and Nutrients
- Hot, Cold, Excluded and Immunosuppressive Tumors
- TME and Immunotherapy
- How the TME Can Contribute to Treatment Resistance
- TME Biomarkers and How the Microenvironment Is Studied
- Can the Tumor Microenvironment Be Targeted?
- The TME in a Systems-Oncology Framework
- Evidence Framework: From Mechanism to Clinical Practice
- Frequently Asked Questions
- References
What Is the Tumor Microenvironment?
The tumor microenvironment is the local biological environment in and around a tumor. It contains both malignant and non-malignant components.
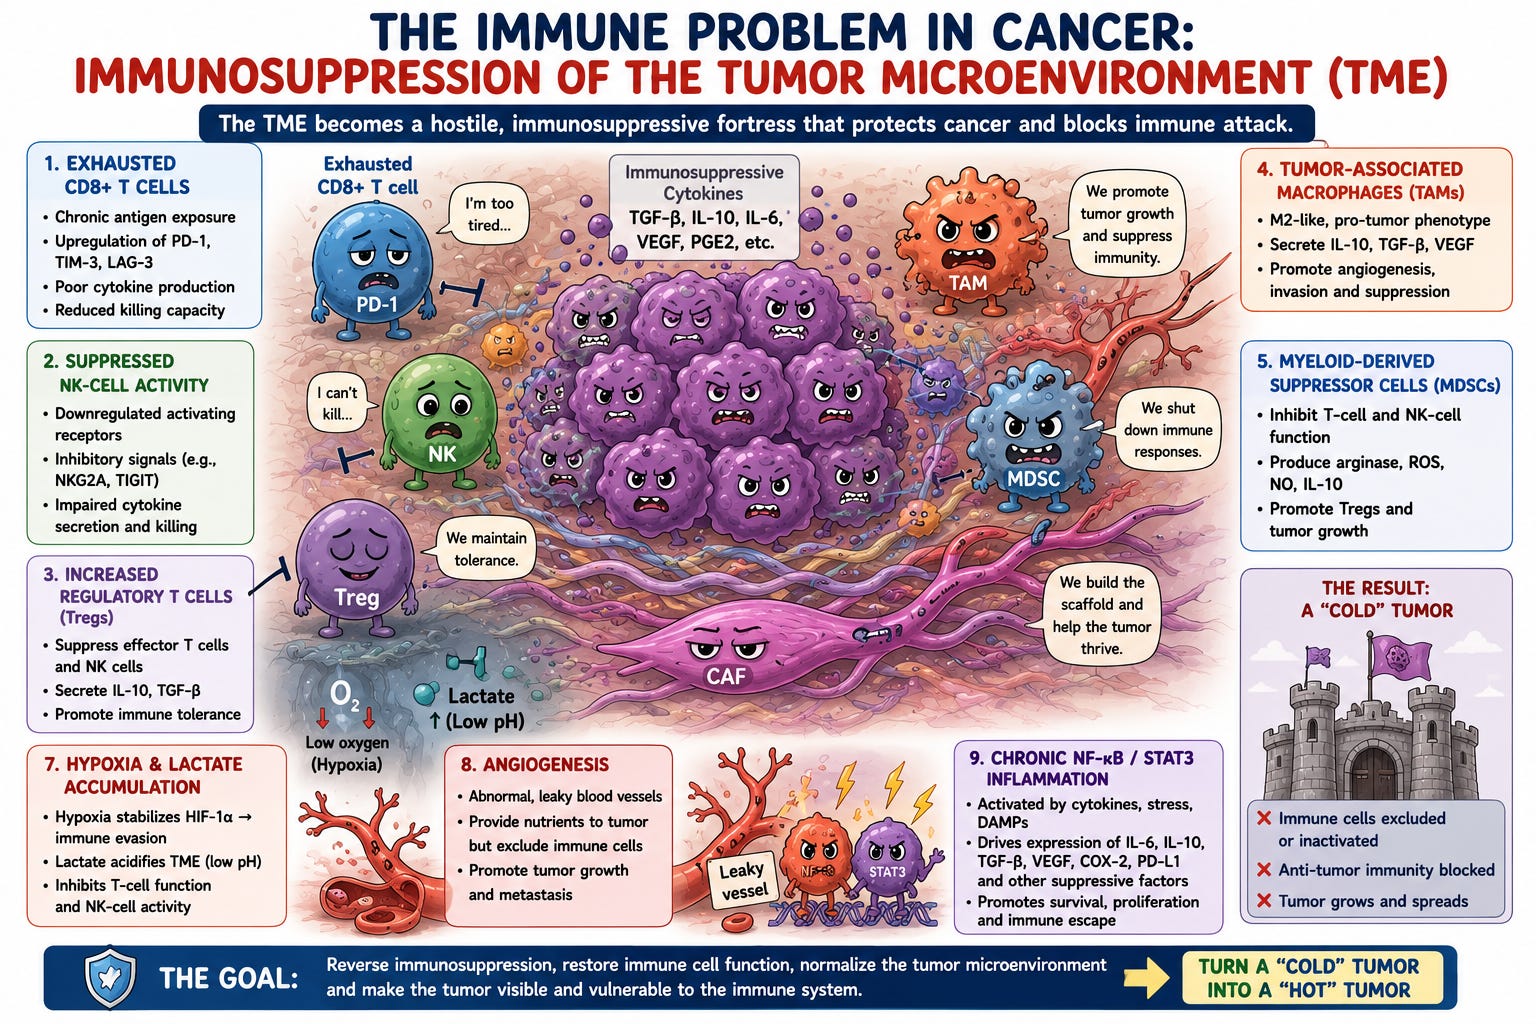 |
| Source: paulmarik.substack.com |
These components communicate through:
- Cell-to-cell contact
- Cytokines and chemokines
- Growth factors
- Extracellular matrix proteins
- Metabolic substrates and waste products
- Oxygen gradients
- Acid-base changes
- Blood-flow and vascular signals
- Mechanical forces and tissue stiffness
The result is not a static environment. It is a continuously changing ecosystem.
As tumor cells proliferate, they consume nutrients and oxygen, release signaling molecules and metabolites, alter surrounding connective tissue, stimulate new blood-vessel formation and recruit immune and stromal cells. Those surrounding cells can then send signals back to the tumor.
The TME is therefore a two-way system.
Cancer cells reshape their environment, while the environment reshapes cancer-cell behavior.
This feedback loop helps explain why two tumors with similar-looking cancer cells under a microscope can sometimes behave differently or respond differently to treatment.
Research into the TME has also shown why measuring only one molecular feature may fail to capture the full biology of a tumor. Location, cell composition, cellular state and interactions between cell populations can matter as much as the presence or absence of an individual biomarker.
The Major Components of the TME
| Component | Examples | Potential role in cancer biology |
|---|---|---|
| Cancer cells | Malignant epithelial or other transformed cells | Growth, invasion, antigen production, metabolic remodeling and secretion of signaling molecules |
| T cells | CD8+ cytotoxic T cells, CD4+ subsets, regulatory T cells | Can mediate tumor killing or suppress anti-tumor immunity depending on population and state |
| B cells | B lymphocytes, plasma-cell populations | Antibody production, antigen presentation and organization of local immune responses |
| Natural killer cells | NK cells | Innate immune recognition and cytotoxicity |
| Dendritic cells | Antigen-presenting cells | Important for antigen presentation and T-cell activation |
| Macrophages | Tumor-associated macrophages | Can participate in inflammation, angiogenesis, tissue remodeling and immune suppression |
| MDSCs | Myeloid-derived suppressor cells | Can suppress effector immune responses and reinforce an immunosuppressive TME |
| CAFs | Cancer-associated fibroblasts | ECM remodeling, fibrosis, signaling, immune exclusion, invasion and metabolic interactions |
| Endothelial cells | Tumor-associated endothelial cells | Form abnormal vessels and influence oxygen delivery and immune-cell trafficking |
| Extracellular matrix | Collagen, fibronectin, laminins and other matrix proteins | Provides structural support and biochemical/mechanical signals; excessive matrix can create physical barriers |
| Metabolites | Lactate, adenosine, kynurenine and others | Can alter immune-cell function and create metabolic competition |
| Physical conditions | Hypoxia, acidity, interstitial pressure, tissue stiffness | Influence cell signaling, immune function, vascular function and drug penetration |
The immune component of the TME is often referred to as the tumor immune microenvironment (TIME). The broader TME includes this immune compartment plus stromal, vascular, extracellular and metabolic components.
The Tumor Immune Microenvironment
The immune system can recognize and attack cancer cells, but tumors can develop local conditions that weaken that response.
Research on the immune contexture of tumors looks beyond simply asking whether immune cells are present. It considers their:
- Density: How many immune cells are present?
- Composition: Which types of immune cells are present?
- Location: Are they inside the tumor, around its margin or excluded from it?
- Functional state: Are they activated, exhausted, regulatory or otherwise suppressed?
- Organization: Do immune cells form structured communities such as tertiary lymphoid structures?
This distinction is important because immune-cell quantity alone does not necessarily describe immune function.
CD8+ T cells
CD8+ cytotoxic T cells can recognize tumor-associated antigens presented on major histocompatibility complex class I molecules and kill target cells.
However, CD8+ T cells within a tumor may encounter an environment characterized by checkpoint signaling, nutrient competition, hypoxia, suppressive cytokines and other factors that impair their activity.
Therefore, a tumor containing CD8+ T cells is not automatically a tumor with an effective anti-cancer immune response.
Regulatory T cells
Regulatory T cells, commonly called Tregs, are important for maintaining immune tolerance. Within certain tumor environments, an abundance of suppressive regulatory populations may contribute to reduced anti-tumor immune activity.
Tumor-associated macrophages
Tumor-associated macrophages (TAMs) are highly adaptable myeloid cells. Their biology is more complicated than the simple older M1-versus-M2 model often used in introductory explanations.
Different macrophage states can perform different functions depending on tumor type, location, signals and treatment history.
Some macrophage populations can support inflammation and immune activity, while others can contribute to angiogenesis, tissue remodeling and immune suppression.
Myeloid-derived suppressor cells
Myeloid-derived suppressor cells (MDSCs) are another important immunosuppressive population. Recent reviews describe their interactions with tumor cells, immune cells, fibroblasts, endothelial cells and metabolic pathways.
MDSCs can suppress anti-tumor immune responses while also participating in a broader tumor-supportive network.
Recent review: MDSCs in the tumor microenvironment
Cancer-Associated Fibroblasts and the Extracellular Matrix
Cancer-associated fibroblasts (CAFs) are one of the major stromal populations in many solid tumors.
CAFs can produce and remodel the extracellular matrix and release signaling molecules that influence tumor cells, immune cells and blood vessels.
Instead of viewing CAFs as one uniform cell type, modern research recognizes substantial heterogeneity among fibroblast populations.
Different CAF states may have different effects on:
- Extracellular matrix deposition
- Fibrosis and tissue stiffness
- Tumor invasion
- Angiogenesis
- Immune-cell recruitment
- T-cell exclusion
- Metabolic exchange
- Metastatic niche formation
A particularly important concept is the relationship between CAFs and the extracellular matrix (ECM).
Excessive deposition and remodeling of collagen-rich matrix can change the physical properties of the tumor. Dense stromal tissue may also alter blood-vessel compression and the movement of drugs or immune cells through the tumor.
Why CAFs matter: A drug may reach the bloodstream perfectly well and still have difficulty reaching every cancer cell inside a dense, poorly perfused, fibrotic tumor.
CAFs are therefore being studied as potential contributors to invasion, metastasis, immune exclusion and therapy resistance.
Cancer-Associated Fibroblasts: Master Tumor Microenvironment Modifiers
Review of CAFs and tumor metastasis
Tumor Blood Vessels and Vascular Dysfunction
Tumors need oxygen and nutrients, but their blood vessels are often structurally and functionally abnormal.
Compared with normal vasculature, tumor-associated vessels can be irregular, immature, leaky and poorly organized. Perfusion may therefore be uneven.
This can create a chain reaction:
Abnormal vessels → uneven perfusion → hypoxia → metabolic stress → immune suppression → altered treatment response
Vascular dysfunction can also influence how immune cells enter a tumor.
For an effective anti-tumor response, lymphocytes need to reach the tumor, cross the endothelial barrier and function within the local tissue. Abnormal tumor vasculature can interfere with these processes.
Research into vascular normalization therefore asks whether appropriately modulating abnormal tumor vessels can improve perfusion and immune-cell access without simply eliminating blood vessels altogether.
This distinction matters because extreme vascular disruption can theoretically worsen hypoxia and reduce delivery of oxygen, drugs and immune cells. The biological objective in many experimental models is therefore not necessarily "remove all vessels" but to modify abnormal vascular function.
Vascular Microenvironment, Tumor Immunity and Immunotherapy
Targeting vascular normalization and immune-vascular crosstalk
Hypoxia and HIF Signaling
Hypoxia means low oxygen availability. It is a common feature of many solid tumors because rapidly growing malignant tissue can outpace the ability of abnormal blood vessels to deliver oxygen evenly.
Cells respond to low oxygen through signaling pathways involving hypoxia-inducible factors (HIFs).
HIF signaling can influence:
- Glycolysis and glucose utilization
- Angiogenic signaling
- Cell survival
- Metastatic behavior
- Extracellular matrix remodeling
- Immune-cell function
- Metabolite production
Hypoxia is particularly important because it connects several apparently different features of cancer biology.
| Hypoxic effect | Potential consequence |
|---|---|
| HIF activation | Changes transcriptional programs involved in adaptation to low oxygen |
| Increased glycolytic activity | Greater glucose consumption and lactate production |
| Angiogenic signaling | Promotion of abnormal blood-vessel formation |
| Metabolic stress | Competition for nutrients between tumor and immune cells |
| Immune remodeling | Altered activity of T cells, NK cells, macrophages and other immune populations |
| ECM and stromal changes | Potential contribution to fibrosis, stiffness and invasion |
| Treatment resistance | Can reduce treatment effectiveness through multiple biological and physical mechanisms |
Hypoxia is therefore not simply "a lack of oxygen." It is a signaling state that can reshape the entire tumor ecosystem.
2025 review: Hypoxic link between cancer cells and the immune system
2026 review: Hypoxia and HIF signaling in the TME
The Metabolic TME: Glucose, Lactate, Adenosine and Nutrients
The TME is also a metabolic environment.
Cancer cells can alter nutrient consumption and metabolite production in ways that affect surrounding cells. At the same time, immune cells and stromal cells have their own metabolic requirements.
This creates a form of metabolic competition and cooperation.
Glucose competition
Activated immune cells require energy and biosynthetic substrates. Tumor cells can consume substantial amounts of glucose, particularly in tumors with high glycolytic activity.
When nutrients become scarce, different cell populations compete for the remaining resources.
Lactate
Lactate is one of the most studied metabolites in the TME.
High glycolytic activity can increase lactate production and export. Lactate does more than represent a metabolic waste product; it can influence the local immune and metabolic environment.
Research has associated elevated lactate with impaired effector function of immune cells and with recruitment or support of immunosuppressive populations.
However, lactate biology is complex. Lactate can act as a metabolic substrate and signaling molecule, and its effects can depend on concentration, cellular context, transport mechanisms and the broader metabolic state of the tumor.
Lactate in the tumour microenvironment: From immune modulation to therapy
2025 review of lactate and immune-cell function
Adenosine
Adenosine is another important immunoregulatory metabolite in the TME.
Hypoxic and stressed tissues can increase extracellular adenosine signaling. In tumors, adenosine pathways have been investigated as contributors to immune suppression and as potential therapeutic targets.
Kynurenine and tryptophan metabolism
Tryptophan metabolism is another metabolic-immune interface. Pathways involving enzymes such as IDO1 can alter local tryptophan availability and generate metabolites that influence immune-cell function.
The broader point is that tumor metabolism and tumor immunity cannot always be studied independently.
Recent reviews increasingly describe the TME as a metabolic battleground involving glucose, amino acids, lipids, lactate, adenosine and other metabolites.
2026 review: Targeting the cancer metabolism-immunity interface
Hot, Cold, Excluded and Immunosuppressive Tumors
One way researchers describe tumor immune states is through simplified categories such as hot, cold, immune-excluded and immune-suppressive.
These terms are useful conceptually, but they are not interchangeable with a formal diagnosis.
| Concept | General biological description | Potential challenge |
|---|---|---|
| Immune-infiltrated / "hot" | Substantial immune-cell infiltration and evidence of an existing immune response | Immune cells may still be dysfunctional, exhausted or suppressed |
| Immune-desert / "cold" | Few immune cells reach the tumor | Limited pre-existing anti-tumor immunity may make some immune therapies harder to activate |
| Immune-excluded | Immune cells may be present around the tumor but have limited penetration into tumor nests | Stroma, vessels and chemokine signaling may restrict access |
| Immune-suppressive | Immune cells are present but the local environment strongly inhibits effective anti-tumor activity | Checkpoint blockade alone may not overcome all suppressive mechanisms |
These classifications are best viewed as biological models rather than rigid patient categories.
A single tumor can also contain multiple niches. One region may be highly inflamed while another is hypoxic, fibrotic and relatively immune-excluded.
The Tumor Microenvironment and Immunotherapy
Immune checkpoint inhibitors have changed treatment for multiple cancer types by releasing inhibitory immune signaling pathways such as PD-1/PD-L1 and CTLA-4.
But checkpoint inhibition does not operate in a biological vacuum.
The TME can affect immunotherapy through several mechanisms.
| TME barrier | How it may affect immunotherapy |
|---|---|
| Low immune infiltration | There may be relatively few effector immune cells available to reactivate |
| Checkpoint expression | Persistent inhibitory signaling can suppress T-cell activity |
| Regulatory T cells | Can suppress local immune responses |
| TAMs | Some macrophage states can create immunosuppressive conditions |
| MDSCs | Can suppress T-cell and NK-cell functions |
| Dense ECM / CAFs | Can contribute to immune-cell exclusion and abnormal tissue structure |
| Abnormal blood vessels | Can interfere with immune-cell trafficking and perfusion |
| Hypoxia | Can change immune-cell function and metabolism |
| Lactate / adenosine | Can alter immune-cell metabolism and suppress effector function |
| Nutrient deprivation | Can create metabolic competition between cancer and immune cells |
This helps explain why some patients with apparently targetable tumors experience limited benefit from immunotherapy, while others with similar tumor types can experience substantial and durable responses.
It also explains the growing interest in combination strategies designed to modify more than one layer of the tumor ecosystem.
Systems-oncology principle: Releasing one immune checkpoint may not be sufficient when physical, vascular, metabolic and cellular barriers are simultaneously suppressing immunity.
2025 review: Immune checkpoint inhibitors and the immunosuppressive TME
Tertiary Lymphoid Structures: An Emerging TME Biomarker
Tertiary lymphoid structures (TLS) are organized aggregates of immune cells that can form in non-lymphoid tissues, including tumors.
Researchers are increasingly studying TLS because their presence, organization and maturity have been associated with anti-tumor immune activity and, in some cancers, with response to immune checkpoint blockade.
However, TLS are heterogeneous.
Their biological significance may depend on:
- Presence or absence
- Density
- Location
- Maturity
- Cellular composition
- Presence of germinal-center-like structures
This means "TLS positive" should not automatically be interpreted as a universal predictor of treatment response.
Standardized definitions and prospective clinical validation remain important areas of research.
Tertiary lymphoid structures: new immunotherapy biomarker
2026 review of TLS as predictive and prognostic biomarkers
How the TME Can Contribute to Cancer Treatment Resistance
Treatment resistance is often discussed as if the cancer cell simply "mutated around the drug." That is only part of the story.
Resistance can result from tumor-cell genetics, altered signaling, epigenetic adaptation, drug metabolism, immune escape and changes in the surrounding microenvironment.
1. Physical resistance
A dense extracellular matrix or high interstitial pressure may affect the movement of therapeutic agents through tissue.
2. Vascular resistance
Abnormal blood vessels can produce uneven perfusion and create regions that receive less oxygen and potentially less drug.
3. Hypoxic resistance
Low oxygen can alter cellular signaling and metabolism and can affect sensitivity to certain therapies.
4. Metabolic resistance
Changes in glucose utilization, lactate, amino-acid metabolism and mitochondrial function can allow tumor and stromal cells to adapt to therapeutic stress.
5. Immune resistance
T cells may be excluded, exhausted or metabolically suppressed. MDSCs, regulatory cells and certain macrophage populations may reinforce immune suppression.
6. Bypass signaling
Cells surrounding a tumor can secrete growth factors and other signals that activate alternative pathways after targeted therapy suppresses a dominant oncogenic pathway.
7. Evolution of the ecosystem
Treatment itself can change the composition of the TME. Surviving tumor cells may interact with a remodeled environment that differs from the pretreatment tumor.
This is particularly important in relapsed or progressive disease.
Resistance is dynamic. The biology of a tumor at diagnosis may not be identical to the biology of the same cancer after chemotherapy, targeted therapy, radiation or immunotherapy.
Recent research emphasizes that spatial and temporal heterogeneity can make cancer resistance difficult to understand using a single biopsy or single molecular measurement.
Dynamic spatial heterogeneity within tumor microenvironments
Spatial oncology: Translating contextual biology to the clinic
TME Biomarkers: What Can Be Measured?
The TME can be studied at multiple levels. No single test captures the entire microenvironment.
| Method | What it can examine | Main limitation |
|---|---|---|
| Routine histology | Tissue architecture, tumor morphology, fibrosis and general cellular patterns | Limited molecular and cellular resolution |
| IHC | Specific proteins such as PD-L1 and selected immune or stromal markers | Usually limited number of markers and spatial complexity |
| Multiplex IHC / IF | Multiple cell populations and markers in the same tissue section | Requires technical validation, specialized analysis and standardized interpretation |
| Flow cytometry | Detailed immune-cell phenotypes and functional markers | Tissue architecture and spatial relationships are largely lost |
| Bulk RNA sequencing | Gene-expression patterns from a tissue sample | Signals from different cell populations are mixed together |
| Single-cell sequencing | Cellular populations and molecular states at single-cell level | Expensive, technically complex and often loses spatial context |
| Spatial transcriptomics | Gene expression mapped to tissue location | Technically demanding and still developing for routine clinical use |
| Spatial proteomics | Protein expression and spatial relationships | Specialized platforms and analytical requirements |
| Digital pathology | Quantitative assessment of cell density, location and tissue architecture | Requires validated algorithms, image quality and standardized interpretation |
Traditional pathology remains fundamental, but newer multiplex and spatial approaches are expanding what can be learned from a tissue sample.
Multiplex imaging can simultaneously evaluate multiple markers and preserve spatial information, allowing researchers to investigate not only which cells are present but where they are relative to one another.
Multiplex immunohistochemistry and immunofluorescence: practical update
2025 review of multiplex IHC and image analysis
Spatial transcriptomics similarly preserves tissue location while measuring gene-expression patterns, offering a way to study tumor and microenvironmental biology in context.
Spatial omics and profiling the tumor microenvironment
Common TME-related biomarkers and signals
| Marker / feature | Biological context | Interpretation |
|---|---|---|
| PD-L1 | Immune checkpoint signaling | Used in selected cancer types and treatment decisions, but interpretation depends on cancer type, assay and clinical setting |
| CD8 | Cytotoxic T-cell infiltration | Provides information about immune infiltration; quantity alone does not establish immune effectiveness |
| FOXP3 | Regulatory T-cell biology | Can help characterize regulatory immune populations |
| CD68 / CD163 | Macrophage populations | Can contribute to characterization of macrophage-rich environments, but individual markers do not completely define macrophage function |
| FAP | Fibroblast biology | Used in research to identify subsets of activated fibroblast populations |
| α-SMA | Activated stromal / myofibroblast phenotype | Can be part of stromal characterization |
| HIF-1α | Hypoxia signaling | Research marker for hypoxia-associated biology; interpretation is context dependent |
| CAIX | Hypoxia and pH regulation | Can indicate hypoxia-associated cellular adaptation in some settings |
| GLUT1 / glycolytic markers | Metabolic adaptation | May provide information about altered glucose metabolism but are not standalone measures of the entire metabolic TME |
| CD39 / CD73 | Adenosine pathway | Research markers of extracellular purine metabolism and immunoregulation |
| TLS features | Organized local immune response | Emerging prognostic and immunotherapy biomarker area; standardization remains important |
Biomarker caution: A biomarker is not automatically a treatment target, a predictive biomarker or a validated clinical decision tool. Its meaning depends on the cancer type, assay, threshold, treatment and clinical context.
Can the Tumor Microenvironment Be Targeted?
Yes. The TME is already part of the mechanism of action or therapeutic rationale for several established cancer strategies, while many other approaches remain investigational.
The distinction between clinically established and experimental TME targeting is essential.
| TME target or strategy | Example biological objective | Evidence / clinical status |
|---|---|---|
| PD-1 / PD-L1 checkpoint blockade | Restore anti-tumor T-cell activity by interrupting inhibitory signaling | Established therapy in multiple cancer types, with indications dependent on tumor type and clinical context |
| CTLA-4 blockade | Modulate T-cell activation and immune regulation | Established in selected cancers and treatment settings |
| Anti-angiogenic therapy | Reduce abnormal angiogenic signaling and, in some contexts, modify vascular function | Established in multiple cancer settings; effects on immune microenvironment depend on drug, tumor and regimen |
| CAF / FAP targeting | Modify fibroblast-rich or stromal environments | Active research area; not a universal standard treatment |
| TGF-β pathway targeting | Reduce immunosuppressive and stromal signaling | Investigational across many cancer settings |
| CSF1 / CSF1R pathway targeting | Alter macrophage biology | Investigational; clinical development has produced mixed results across settings |
| Adenosine-pathway inhibition | Reduce metabolically mediated immune suppression | Investigational |
| IDO1 / tryptophan pathway targeting | Modify immunosuppressive metabolism | Investigational; clinical development has faced challenges |
| Lactate / MCT targeting | Alter metabolic and immune effects of lactate | Predominantly preclinical or early translational research |
| Hypoxia-directed therapies | Exploit or modify low-oxygen tumor regions | Active research area with context-dependent clinical development |
| TME normalization | Improve vascular, stromal and immune conditions rather than targeting cancer cells alone | Important translational concept; clinical application depends on the specific intervention |
The central idea is increasingly described as microenvironmental reprogramming: changing the conditions around cancer cells so that conventional treatment or immune attack can work more effectively.
However, the TME is highly interconnected. Blocking one pathway can activate compensatory mechanisms elsewhere. This is one reason many TME-directed therapies are being investigated as combinations rather than universal stand-alone treatments.
The TME in a Systems-Oncology Framework
A useful way to understand modern oncology is to treat the tumor as an interacting system rather than as a single molecular target.
A simplified systems model is:
Tumor genotype → signaling pathways → cellular phenotype → metabolism → microenvironment → immune response → treatment pressure → adaptation → resistance
Each layer can influence the others.
For example:
- A mutation may alter signaling and increase glucose consumption.
- Higher glucose consumption can contribute to local nutrient competition.
- Increased glycolysis can increase lactate production.
- Lactate and hypoxia can alter immune-cell behavior.
- CAFs may remodel the surrounding matrix and influence immune-cell trafficking.
- Abnormal blood vessels may worsen hypoxia and drug-delivery problems.
- Treatment may eliminate sensitive clones while selecting resistant populations living within a remodeled ecosystem.
This is why treatment resistance should not always be reduced to a single mutation.
The clinically meaningful question may instead be:
What combination of tumor-cell biology, immune state, stromal architecture, vascular status and metabolic conditions is sustaining this cancer right now?
Explore the Cancer Treatment Resistance Atlas for a broader biomarker × mechanism × resistance × next-treatment framework.
Explore Metabolic Oncology to examine how tumor metabolism intersects with the TME.
Explore Cancer Immunotherapy for PD-1, PD-L1, CTLA-4 and emerging immune checkpoints.
TME Biomarker × Mechanism × Treatment-Relevance Matrix
| TME feature | Mechanism of interest | Potential clinical question | Current evidence position |
|---|---|---|---|
| Low CD8+ infiltration | Limited effector immune presence | Is the tumor immune-infiltrated enough for immune-based strategies to have a biological foothold? | Biologically important; clinical interpretation varies by cancer and assay |
| High PD-L1 | PD-1/PD-L1 inhibitory signaling | Does the approved clinical setting support checkpoint inhibitor use? | Clinically relevant in selected cancers and indications |
| Dense CAF-rich stroma | ECM remodeling and immune exclusion | Could stromal architecture be contributing to treatment resistance? | Strong research interest; not a universal routine treatment-selection marker |
| Hypoxia-associated markers | HIF-driven adaptation | Could hypoxia be contributing to aggressive biology or therapeutic resistance? | Strong biological evidence; clinical implementation varies |
| High lactate / glycolytic phenotype | Metabolic-immune suppression | Is altered tumor metabolism affecting immune function? | Strong mechanistic and translational research; treatment targeting remains investigational in many settings |
| High MDSC burden | Myeloid-mediated immune suppression | Could myeloid suppression be limiting immunotherapy activity? | Important research biomarker; not universally standardized for routine treatment selection |
| TAM-rich environment | Macrophage-mediated immune and stromal signaling | Is macrophage biology contributing to progression or immune resistance? | Active biomarker and therapeutic research |
| TLS-positive environment | Organized local adaptive immunity | Does the tumor have a structured immune niche associated with treatment response? | Promising emerging biomarker; standardization and prospective validation continue |
| Abnormal tumor vasculature | Hypoxia, perfusion and immune trafficking | Could vascular dysfunction contribute to poor drug or immune-cell access? | Established biological concept; intervention remains cancer- and regimen-specific |
Evidence Framework: From Mechanism to Clinical Practice
The TME contains an enormous amount of exciting laboratory research. But a biological mechanism does not automatically become a clinically useful treatment.
For patient-facing cancer information, it is useful to separate evidence into levels.
| Evidence level | What it generally means | How to interpret it |
|---|---|---|
| E0 | Basic mechanistic hypothesis | Useful for understanding biology, but not evidence that a therapy works in patients |
| E1 | Cell, organoid or animal research | Can demonstrate mechanism and generate hypotheses |
| E2 | Observational human evidence or retrospective tissue studies | Can reveal associations but usually cannot establish causation |
| E3 | Early prospective clinical evidence | Provides human treatment data but may have small samples or limited controls |
| E4 | Randomized controlled clinical evidence | Stronger evidence for treatment effects when appropriately designed and powered |
| E5 | Consistent clinical evidence incorporated into authoritative guidelines or established practice | Represents the highest level of practical clinical maturity in this framework |
This framework is especially useful for TME research because the field contains many promising targets that remain experimental.
For example, a study may show that blocking a metabolic enzyme improves T-cell activity in cell culture. That can be scientifically important. But it does not demonstrate that administering an inhibitor to a patient with advanced cancer improves survival.
Likewise, a retrospective study may find that a specific TME feature is associated with better outcomes. That does not necessarily mean that deliberately changing that feature will improve the outcome.
Association is not intervention. A biomarker associated with treatment response is not automatically a treatment target.
What Does TME Analysis Mean for a Patient?
For an individual patient, the relevance of TME biology depends heavily on the cancer type, stage, treatment history and available tissue.
In routine oncology, doctors may already consider several components that overlap with the broader TME concept, including:
- PD-L1 expression where clinically relevant
- Mismatch-repair or microsatellite-instability status
- Tumor mutational burden in selected settings
- Tumor-infiltrating immune cells in specific cancers
- Histologic features of the tumor and its stroma
- Vascular and anatomical characteristics visible on imaging or pathology
- Prior response or resistance to immunotherapy or targeted therapy
More advanced TME characterization may involve research-oriented tissue profiling, multiplex immunohistochemistry, spatial transcriptomics, single-cell sequencing or other multi-omic technologies.
These approaches can provide much richer biological information, but they are not automatically part of routine clinical care for every cancer patient.
Why biopsy timing matters
A biopsy provides a snapshot of a particular location at a particular time.
Because tumors are spatially heterogeneous, one sample may not represent every region of the tumor or every metastatic site.
Treatment can also change the TME.
Therefore, when disease has progressed after treatment, clinicians may sometimes consider whether additional tissue or molecular testing is clinically appropriate rather than assuming that the original sample remains a perfect representation of current disease biology.
Clinical decisions should be based on validated tests and the patient's specific cancer setting rather than on experimental TME concepts alone.
TME and the Cancer Treatment Resistance Atlas
The TME can be incorporated directly into a treatment-resistance matrix.
| Resistance mechanism | TME contributor | Examples of biological signals | Research direction |
|---|---|---|---|
| Immune exclusion | CAFs, ECM, abnormal endothelium | TGF-β, CXCL12 and matrix remodeling | Stromal and vascular modulation |
| Immune suppression | Tregs, MDSCs, TAMs | IL-10, TGF-β, arginase-related pathways and checkpoint signaling | Myeloid and immune reprogramming |
| Metabolic suppression | Tumor cells, stromal cells | Lactate, adenosine, glucose competition, kynurenine | Metabolic-immunologic combinations |
| Hypoxia | Abnormal vessels, high metabolic demand | HIF signaling, VEGF, hypoxia-associated metabolism | Hypoxia-directed and vascular approaches |
| Poor drug penetration | Dense ECM, abnormal perfusion, interstitial pressure | Collagen-rich matrix, vascular dysfunction | Drug-delivery and stromal remodeling strategies |
| Alternative growth signaling | Stromal and immune-derived growth factors | HGF, FGF, EGF and cytokine signaling | Combination targeted therapies |
| Post-treatment ecosystem remodeling | Changes in immune and stromal populations | Altered cellular composition and spatial niches | Longitudinal and spatial profiling |
This framework emphasizes an important principle:
The same resistance phenotype may arise from different mechanisms in different cancers.
For this reason, a TME strategy should be connected to cancer type, molecular subtype, treatment history and evidence level rather than treated as a universal protocol.
Where TME Research Is Going
The next phase of TME research is moving from simple cell counting toward spatial and systems-level analysis.
Researchers increasingly want to know:
- Which cells are present?
- Where are they located?
- Which cells are communicating?
- What metabolic resources are available?
- Which regions are hypoxic?
- Where are immune cells being excluded?
- Which microenvironmental niches contain resistant tumor cells?
- How does the ecosystem change during treatment?
Single-cell and spatial technologies are particularly important because conventional bulk sequencing averages together multiple cellular populations and therefore may miss local relationships.
Spatial oncology attempts to restore this lost context.
Spatial transcriptomics and tumor-microenvironment crosstalk
Spatial oncology and clinical translation
The longer-term goal is a more complete tumor ecosystem map that integrates:
Genomics + transcriptomics + proteomics + immune profiling + spatial biology + metabolism + imaging + treatment history
Such integration could eventually make it possible to identify not just the tumor's dominant mutation, but also the local ecosystem that allows that tumor to survive.
The Big Picture: Cancer Is an Ecosystem
The tumor microenvironment helps explain why cancer is more complicated than a list of mutations.
A tumor is embedded in living tissue.
It interacts with blood vessels, fibroblasts, immune cells, extracellular matrix, metabolites, oxygen gradients and signaling pathways. Those interactions evolve as the cancer grows and as treatment changes the ecosystem.
That leads to a more complete model of cancer:
Cancer = malignant cells + surrounding ecosystem + evolutionary pressure + treatment response
This perspective does not replace conventional oncology. Instead, it adds another layer of biological context.
The practical significance of the TME is therefore not that every component needs to be "treated." Rather, understanding the TME can help researchers and clinicians ask better questions about why a tumor behaves differently, why an immune therapy succeeds or fails, why metastatic lesions may differ from the primary tumor, and why resistance develops.
Tumor Microenvironment: 10 Key Takeaways
- The TME is the ecosystem surrounding a tumor. It includes immune cells, fibroblasts, blood vessels, extracellular matrix, metabolites and signaling molecules.
- The tumor and its environment constantly influence each other.
- Immune contexture matters. Location and functional state can be as important as immune-cell quantity.
- CAFs and extracellular matrix can influence immune exclusion, tissue structure and metastasis.
- Abnormal tumor blood vessels can contribute to hypoxia, impaired perfusion and immune dysfunction.
- Hypoxia is a signaling state, not simply low oxygen. HIF pathways can connect metabolism, angiogenesis and immune regulation.
- Metabolism and immunity are interconnected. Lactate, adenosine, glucose competition and other metabolic pathways can shape immune function.
- The TME can contribute to treatment resistance. Resistance can involve physical, metabolic, vascular, immune and signaling mechanisms.
- Spatial biology is changing how researchers study tumors. Where cells are located may be as important as which cells are present.
- TME research is promising but highly context dependent. A mechanism demonstrated in the laboratory is not automatically a validated clinical treatment.
Frequently Asked Questions About the Tumor Microenvironment
What is the tumor microenvironment in simple terms?
The tumor microenvironment is everything around a cancer cell that can influence its behavior. It includes immune cells, fibroblasts, blood vessels, extracellular matrix, nutrients, metabolites and signaling molecules.
Why is the tumor microenvironment important?
The TME can influence tumor growth, immune recognition, metastasis, drug delivery and treatment resistance. The National Cancer Institute notes that tumors can change their microenvironment and that the microenvironment can affect tumor growth and spread.
What cells are found in the tumor microenvironment?
Depending on the cancer, the TME may contain T cells, B cells, natural killer cells, dendritic cells, macrophages, MDSCs, regulatory T cells, fibroblasts, endothelial cells and other stromal populations.
What are cancer-associated fibroblasts?
Cancer-associated fibroblasts are stromal cells that can remodel extracellular matrix and influence tumor growth, immune-cell behavior, angiogenesis, metabolism and metastasis.
What is a hot tumor?
"Hot" generally refers to a tumor with substantial immune infiltration and evidence of an active immune response. The term is a conceptual classification rather than a universal clinical diagnosis.
What is an immune-excluded tumor?
An immune-excluded tumor contains immune cells around or near the tumor but has limited penetration of those cells into tumor nests. Stromal architecture, chemokine signaling and abnormal vasculature can contribute to this pattern.
Does hypoxia make cancer more difficult to treat?
Hypoxia can contribute to treatment resistance through changes in signaling, metabolism, angiogenesis and immune function. Its importance varies by tumor type and treatment.
Does lactate help cancer cells?
Lactate can influence tumor metabolism and the surrounding immune environment. Research indicates that high lactate concentrations can suppress certain immune effector functions and contribute to an immunosuppressive TME, although lactate biology is complex and context dependent.
Can the tumor microenvironment be tested?
Yes. Depending on the clinical or research setting, testing can include pathology, immunohistochemistry, multiplex imaging, flow cytometry, RNA profiling, single-cell sequencing and spatial transcriptomics. Not all of these tests are routinely available or clinically validated for treatment selection.
Can doctors treat the tumor microenvironment?
Some established cancer therapies affect components of the TME, including immune checkpoint inhibitors and anti-angiogenic therapies. Many other TME-directed approaches, including strategies targeting CAFs, MDSCs, adenosine, lactate or specific stromal pathways, remain investigational.
Does a favorable TME guarantee that immunotherapy will work?
No. Cancer response is determined by multiple interacting factors. TME characteristics may provide useful information, but no single microenvironmental feature guarantees treatment response.
Why can two metastases from the same cancer behave differently?
Different metastatic sites can develop different immune, stromal, vascular and metabolic environments. Spatial and organ-specific differences may therefore contribute to variation in treatment response between lesions.
Editor's Note
The tumor microenvironment is one of the most important concepts for understanding modern cancer biology because it connects several fields that are often discussed separately: tumor genetics, cancer metabolism, immunotherapy, stromal biology, angiogenesis, drug delivery and treatment resistance.
For patients, however, the practical meaning of a TME finding depends on the cancer type, stage, molecular profile, prior treatment and strength of clinical evidence.
Laboratory mechanisms can generate important hypotheses without establishing that a particular intervention improves outcomes in humans. Experimental approaches should therefore be distinguished clearly from treatments supported by clinical evidence and professional guidelines.
Medical disclaimer: This article is for educational and informational purposes only and is not individual medical advice. Cancer treatment should be determined with an appropriately qualified oncology team using the patient's diagnosis, pathology, molecular findings, imaging, treatment history and overall clinical circumstances. Experimental TME-targeted therapies should not be substituted for established cancer treatment without appropriate medical supervision.
References and Further Reading
- National Cancer Institute. Tumor Microenvironment.
- Wu T, et al. Immune contexture defined by single cell technology for prognosis prediction and immunotherapy guidance in cancer. Cancer Communications.
- Implications of the tumor immune microenvironment for staging and therapeutics.
- Cancer-Associated Fibroblasts: Master Tumor Microenvironment Modifiers.
- Unlocking the crucial role of cancer-associated fibroblasts in tumor metastasis: Mechanisms and therapeutic prospects.
- Vascular Microenvironment, Tumor Immunity and Immunotherapy.
- Targeting vascular normalization: a promising strategy to improve immune-vascular crosstalk in cancer immunotherapy.
- Hypoxic link between cancer cells and the immune system: The role of adenosine and lactate.
- Hypoxia and HIF signalling in tumour microenvironment: linking immune evasion, metabolic rewiring and epigenetic regulation.
- Lactate in the tumour microenvironment: From immune modulation to therapy.
- Impact of lactate on immune cell function in the tumor microenvironment.
- Targeting the cancer metabolism-immunity interface: update and perspectives.
- Immune checkpoint inhibitors and immunosuppressive tumor microenvironment: current challenges and strategies to overcome resistance.
- Myeloid-derived suppressor cells in the tumor microenvironment: cellular crosstalk, immunosuppressive effects, and therapeutic targets.
- Tertiary lymphoid structures: new immunotherapy biomarker.
- The Emerging Role of Tertiary Lymphoid Structures as Predictive and Prognostic Biomarkers of Immunotherapy in Cancer.
- Multiplex Immunohistochemistry and Immunofluorescence: A Practical Update for Pathologists.
- Exploring Multiplex Immunohistochemistry Techniques and Histopathology Image Analysis.
- Spatial omics: applications and utility in profiling the tumor microenvironment.
- Spatial oncology: Translating contextual biology to the clinic.
- Defining and modeling dynamic spatial heterogeneity within tumor microenvironments.
Article updated: September 2026. This page is intended as an evolving educational resource because tumor-microenvironment research is rapidly developing.


Comments
Post a Comment